See also
Major paediatric trauma - Primary survey
Major paediatric trauma - Secondary survey
Cervical spine assessment
Child abuse
Key points
- Many head injuries are at very low risk of clinically important traumatic brain injury and can be immediately discharged home
- Moderate to severe head injury requires immediate management, urgent investigation and referral
- Head injury with risk factors or in vulnerable groups require a more considered approach regarding investigation and management
- Consider child abuse in all children with head injury
Background
- Head injury is one of the most common paediatric presentations to emergency departments
- Children who are non-verbal or non-ambulant require a more cautious assessment and may require longer observation
- Observation extends beyond the ED encounter and includes parent assessment and GP review
- Significant head injury may occur without loss of consciousness (LOC)
- Children with suspected drug or alcohol intoxication may be more difficult to assess. Assume conscious level relates to injury and have a lower threshold for referral and neuroimaging
- Concurrent cervical spine assessment is required in all children with head injury
- Children who present late may have a significant head injury. Children who present >24 hours post-injury have higher rates of intracranial injury detected on imaging
Assessment
History
- Medical history
- Bleeding disorders
- Anticoagulation or antiplatelet therapy
- Developmental history, including presence of a neurodevelopmental disorder
- Previous neurosurgical intervention eg ventriculoperitoneal shunt
- Injury
- Timing
- Mechanism
- Circumstances of injury
- Consider medical cause for injury, eg syncope, seizures, hypoglycaemia
- Drug or alcohol intoxication
- Obtain a collateral history if there was loss of consciousness/amnesia
- Take an in-depth history with a moment-by-moment account “What, where, when, how, who?”
- Consider child abuse if the history does not adequately explain the injury
- Clinical course and associated symptoms
- Stable, deteriorating, improving
- Loss or impairment of consciousness, including duration
- Abnormal behaviour including agitation, confusion and drowsiness
- Apnoea or abnormal breathing, particularly in infants
- Headache
- Nausea and vomiting
- Presence of amnesia, both retrograde and antegrade
- Post injury seizure
- Other injuries sustained
- Children who present >24 hours after injury should be risk stratified in the same way as those presenting immediately after the event
Examination
- Complete primary survey
- Neurological examination, including signs of raised intracranial pressure
- Unilateral or bilateral pupillary dilatation
- Drop of more than 2 points in Glasgow coma score (GCS)
- Development of focal neurological signs
- Abnormal posturing
- Irregular respirations, hypertension and bradycardia (Cushing reflex – late sign)
| GCS |
|---|
| ≥4 years | <4 years |
| Response | Score | Response | Score |
| Eye opening | | Eye opening | |
| Spontaneously | 4 | Spontaneously | 4 |
| To verbal stimuli | 3 | To verbal stimuli | 3 |
| To painful stimuli | 2 | To pain | 2 |
| No response to pain | 1 | No response to pain | 1 |
| Best verbal response | | Best verbal response | |
| Orientated and converses | 5 | Alert; babbles, coos, words to usual ability | 5 |
| Confused and converses | 4 | Less than usual words, spontaneous irritable cry | 4 |
| Inappropriate words | 3 | Cries only to pain | 3 |
| Incomprehensible sounds | 2 | Moans to pain | 2 |
| No response to pain | 1 | No response to pain | 1 |
| Best motor response | | Best motor response | |
| Obeys verbal commands | 6 | Spontaneous or obeys verbal commands | 6 |
| Localises to stimuli | 5 | Localises to pain or withdraws to touch | 5 |
| Withdraws to stimuli | 4 | Withdraws from pain | 4 |
| Abnormal flexion to pain (decorticate) | 3 | Abnormal flexion to pain (decorticate) | 3 |
| Abnormal extension to pain (decerebrate) | 2 | Abnormal extension to pain (decerebrate) | 2 |
| No response to pain | 1 | No response to pain | 1 |
- Feel for skull fractures
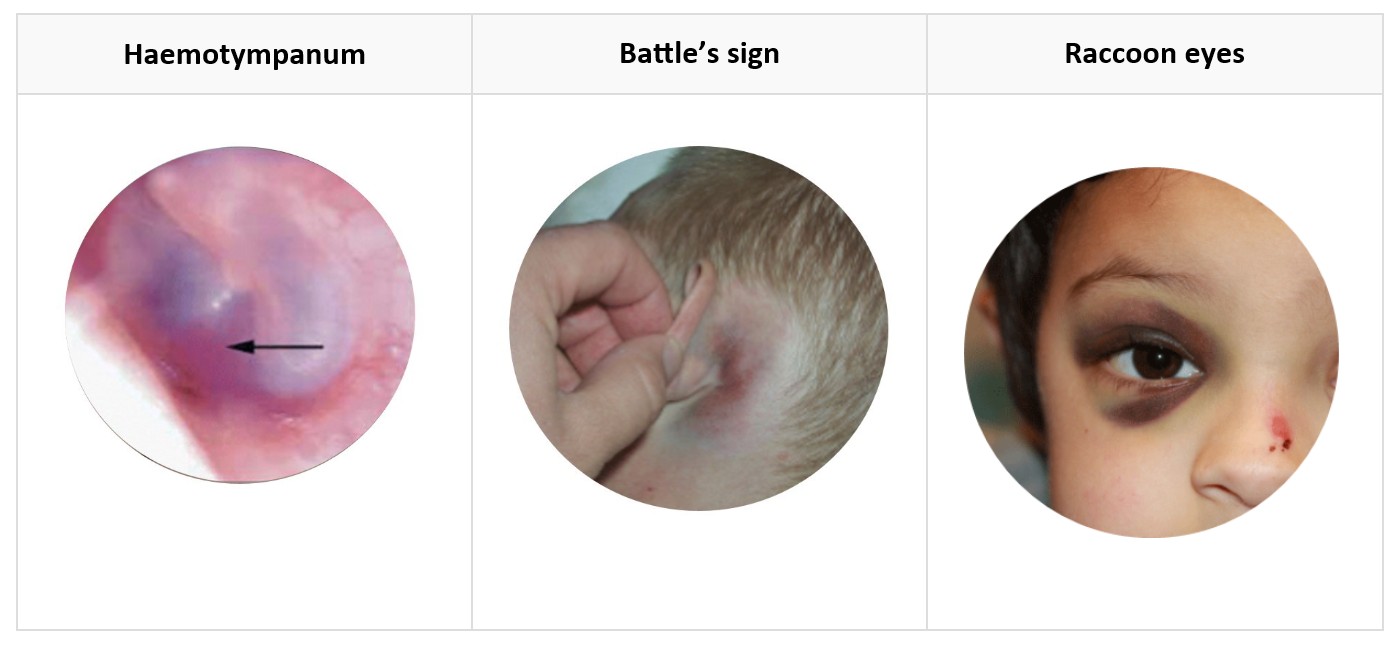
- Look for signs of fractured base of skull
- Haemotympanum
- Periorbital bruising (Raccoon eyes)
- Bruising over mastoid area (Battle sign)
- Cerebrospinal fluid otorrhoea or rhinorrhoea
Initial assessment of severity
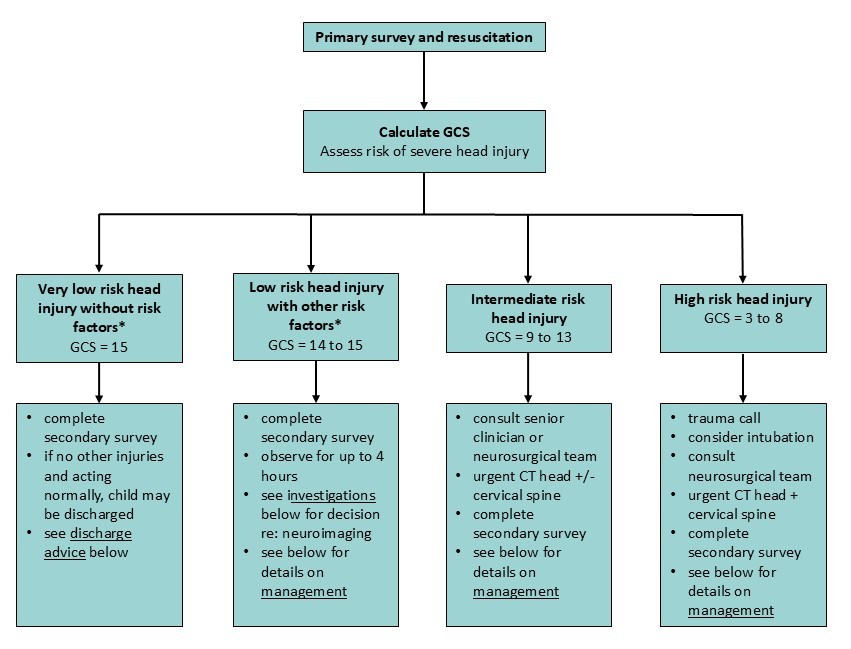
- Determines those that can be discharged promptly, versus those that need a period of observation or those requiring active investigation and management
- Severity may change over time. All children should be regularly reassessed for signs or symptoms of deterioration
- GCS is the key endpoint when stratifying according to risk
Head injury severity stratification and initial management flowchart
Risk factors
| Category | Risk factor |
|---|
| Pre-injury | Bleeding disorder
Anticoagulation/antiplatelet treatment
VP shunt
Neurodevelopmental disorder |
| Mechanism of injury | Suspected child abuse
Severe trauma (eg severe motor vehicle accident, head struck by high impact object)
Fall of ≥1 metre if <2 years
Fall of >1.5 metres if ≥2 years
Head struck by high impact object |
| Post-injury | LOC
Persistent abnormal behaviour
Abnormal neurology
Post-traumatic seizure
Persistent vomiting (>4h post-injury)
Severe headache
Palpable skull fracture
Sign of basal of skull fracture
Non-frontal scalp haematoma (occipital, parietal or temporal) in child <2 years |
Management
Investigations
Neuroimaging
- Discuss neuroimaging with a senior clinician or neurosurgeon. The need and timing depend on balancing clinical benefit against radiation and sedation risks
- CT head is the neuroimaging of choice in emergency departments
- For children with mild head injury, a decision about whether to image should be based on the presence or absence of risk factors (as described above)
- Indications for neuroimaging may evolve during the period of observation
Risk factors as indications for imaging
Definite indications
Risk of clinically important traumatic brain injury (ciTBI): 1 out of 10 | Relative indications (observe child and consider neuroimaging)
Risk of ciTBI: 1 out of 100 |
|---|
Any moderate or severe head injury
(GCS ≤13)
Focal neurological deficit
Signs of base of skull fracture
Palpable skull fracture
Suspected child abuse
Persistent signs of altered mental status | GCS persistently 14
LOC
Post-traumatic seizure (not including immediate “impact” seizure)
Severe headache
Persistent vomiting (>4 hours post-injury)*
Acting abnormally as per parent (<2 years)
Severe mechanism of injury
Non-frontal scalp haematoma (<2 years) |
ciTBI is defined as: need for neurosurgical intervention, need for intubation >24 h, need for hospital admission ≥2 nights, and/or death
Neuroimaging for children with special conditions
Children with any of the following conditions require greater consideration of neuroimaging:
Age <6 months
Bleeding tendency, or taking either anticoagulation or anti-platelet therapy
VP shunt
Neurodevelopmental disorders
Drug or alcohol intoxication |
Isolated vomiting*
- Isolated vomiting in a well appearing child without other risk factors is not commonly associated with ciTBI (<1%). Consider observation rather than immediate CT in these children
- Persistent vomiting (>4 hours post-injury) or ≥4 vomiting episodes warrants reassessment and consideration of imaging
If no other risk factors are present, a period of structured observation may be considered over immediate neuroimaging. Seek advice from a senior clinician, or other relevant expert
Consideration of other investigations
- Plain skull X-ray or head ultrasound should not be performed in lieu of a CT
- If other injuries are present (bruising, fractures), investigate as clinically indicated
- Consider investigation for causes of falls, eg alcohol, other ingestions, arrhythmias, hypoglycaemia, syncope
Treatment
The aim of stratification of head injury is to facilitate timely discharge for those where it is deemed appropriate, whilst ensuring adequate observation, appropriate neuroimaging and escalation
Very low risk head injury (without other risk factors)
- If the child is
- <6 months: consider observation and/or speak with a senior clinician
- ≥6 months: discharge if the child presents with normal GCS and behaving normally
- Treat pain with simple analgesia
- Ensure discharge advice given to parents
Low risk head injury (with other risk factors)
- Child should be observed for up to 4 hours post injury, with
- 30-minutely neurological observations (conscious state, PR, RR, BP, pupils and limb power) for the first 2 hours
- one-hourly neurological observations thereafter
- May be discharged home if there is return to normal conscious state for at least one hour, acting normally and can tolerate oral fluids
- Treat pain with simple analgesia
- Consider antiemetics for vomiting
- A persistent headache, ongoing vomiting, GCS of 14 or persistent altered mental status requires further observation and likely investigation
- Immediate senior medical review is necessary for a GCS drop of ≥2 points
- Consider providing concussion advice
Isolated linear skull fractures
- Consider the possibility of child abuse if the history does not match the injury
- Children with an isolated linear and non-displaced skull fracture, who are otherwise clinically well, are at very low risk of subsequent neurosurgical intervention
- Discuss with neurosurgeon for management and follow-up planning
Intermediate risk head injury
The initial aim of management is to identify significant intracranial injury
- Ensure early discussion with senior ED clinician and/or neurosurgeon
- Urgent CT of head (and consideration of imaging of c-spine if relevant)
- Low threshold to escalate care as per severe head injury below
- Give antiemetics for vomiting
- Consider tranexamic acid (TXA) for children with GCS ≤12
High risk head injury
The initial aim of management is to prevent secondary brain damage. Severe head injury requires immediate neuroprotective measures, urgent neuroimaging and neurosurgical consultation
- Activate the trauma team per local criteria
- Resuscitate patient as required (intubation/ventilation and neuroprotection)
- Organise urgent CT head + c-spine (+/- other regions as relevant)
- Obtain early neurosurgical consultation
- Minimise cervical spine movement until formal assessment. See Cervical spine assessment
- Consider TXA, 15 mg/kg (max 1 g) IV bolus, within 3 hours of injury, ideally before imaging. Discuss with senior clinician or neurosurgeon
- Treat coagulopathy. See Blood product prescription
- Standard neuroprotective measures
- Maintain head position: 30 degrees head up (after correction of shock) with head in midline position to help venous drainage
- Maintain normal sodium and glucose levels. See Hyponatraemia and Hypoglycaemia
- Maintain normal temperature
- Give antiemetics to prevent vomiting, which may increase ICP
Intubation and ventilation
- Consider intubation if
- Child unresponsive or not responding purposefully to pain
- GCS persistently ≤8
- Loss of protective laryngeal reflexes
- Respiratory irregularity or suspected hypoventilation
- If possible, a neurological examination should be performed before intubation and any motor deficits or cranial nerve signs documented
- Ventilate to PaCO2 35-40 mmHg
- Intubation should be performed by the most skilled clinician available. Carefully titrate analgesia and sedation with support from senior clinician
Maintain circulation and cerebral perfusion
- Uncorrected hypotension is a significant factor in secondary brain damage
- Ensure adequate blood pressure with crystalloid infusion (eg 0.9% sodium chloride), blood products or inotropes if necessary
Treat signs of raised ICP
- Involve neurosurgical team early
- Signs of coning include: pupillary changes, abnormal posturing, a rapid decline in GCS, Cushing’s Triad (hypertension, bradycardia, bradypnoea)
- Consider hypertonic saline (sodium chloride 3% 3 mL/kg IV over 10-20 min) or 20% mannitol (0.25-0.5 g/kg IV over 20-30 min)
Control seizures
- Give benzodiazepine immediately if active seizures. See Seizures – acute management
- Discuss seizure prophylaxis with neurosurgery (eg levetiracetam load)
Consider consultation with local paediatric or paediatric neurosurgical team when
- Failure to return to normal within 4 hours
- Suspected child abuse (follow local child protection pathways)
- Uncertainty surrounding when to perform neuroimaging
- Any child with a ventricular shunt
- Any child with a bleeding disorder, or who is taking anticoagulant or anti-platelet therapy (discuss with paediatric haematologist)
Consider transfer to a tertiary centre when
- All head injuries at high risk of severe head injury
- Deteriorating conscious level (especially motor response changes)
- Focal neurological signs
- Seizure without full recovery
- Definite or suspected penetrating injury
- Cerebrospinal fluid leak
- Child abuse
- Child requiring care beyond the comfort level of the hospital
For emergency advice and paediatric or neonatal ICU transfers, call Retrieval Services
Consider discharge from ED when
- The child is acting normally for at least one hour as per the parent, has a normal neurological examination and can tolerate fluids
- There are no other factors warranting admission or longer observation (eg other injuries or underlying medical concerns, drug and alcohol intoxication, social factors, possible child abuse)
Concussion and return to activity
- A concussion is a mild traumatic brain injury that temporarily alters brain function
- Symptoms span four domains
- Physical: headache, nausea, dizziness
- Cognitive: slowed thinking, concentration difficulties
- Emotional: irritability, anxiety
- Sleep disturbance: Difficulty falling or staying asleep, altered sleep length
- Management
- Active recovery, not strict rest: relative rest for 24-48 hours, then light physical activity (eg walking)
- Avoid screen time in the first 48 hours
- Brief and mild symptom exacerbation during activity is acceptable
- Return to school precedes return to sport; most children return to school within 10 days
- Avoid contact/collision sports/high risk activities until medical clearance
- Average time to full return to sport is 20 days
- Generally, very low to low risk head injury can be followed up by a GP
- Intermediate to high risk head injury will often require brain injury rehab follow-up
- Provide a concussion action plan (CAP) at discharge
- Persistent symptoms
- For adolescents with symptoms persisting >10 days post-concussion, cervicovestibular rehabilitation may be of benefit
- Refer children with persistent post-concussion symptoms (≥4 weeks) to local concussion/rehabilitation service
- Resources for clinicians
Parent advice and follow-up
- Ensure the parents have clear instructions regarding the management of their child at home, and when to seek medical attention
- Children discharged following a mild to moderate head injury should consider follow-up with a primary care clinician within 1 to 2 weeks to assess post-concussive symptoms
- Advise parents that children with anything other than a very low risk head injury may take up to 4 weeks to recover, and graded return to activity is recommended
Parent information sheets
Head injury - general advice (Kids Health Info, RCH)
Head Injury - Return to school and sport (Kids Health Info, RCH)
Head injury factsheet (PCH, WA)
Concussion and mild head injury factsheet (SCHN)
How to use a Concussion Action Plan (SCHN)
Concussion Action Plan (<8 years) (SCHN)
Concussion Action Plan (>8 years) (SCHN)
Head injury – ED Discharge advice (Children’s Health QLD)
Raising Children Network Concussion
Concussion in Sport Australia
HeadCheck app: symptom tracking and recovery guidance (MCRI)
Concussion aftercare: Neck strength
Last updated Aug 2026